
Stage 1 colon cancer treatment in India focuses on completely removing the cancer before it has spread to regional lymph nodes or distant organs. For selected very early cancers found within a polyp, complete removal during colonoscopy ($200–$550, day-care) may be sufficient. When endoscopic treatment is not adequate, the standard approach is usually surgical removal of the affected section of the colon along with nearby lymph nodes.
Stage 1 colon cancer is classified as T1 or T2, N0, M0. This means the cancer has invaded the submucosa or muscular layer of the colon but has not been identified in regional lymph nodes or distant organs.
For most patients with adequately treated Stage 1 colon cancer, chemotherapy is not routinely required. The main treatment decision is whether the cancer can be safely and completely removed through colonoscopy or whether a formal colectomy is necessary. GAF Healthcare planning ranges for colectomy are $7,000–$18,000 (typically 5–10 nights). The broader colorectal cancer surgery sheet lists $8,000–$20,000.
This article is the Stage 1 hub for the colon cluster. The broader pathway — later stages, molecular tests and systemic medicines — is in Colon Cancer Treatment in India. How hemicolectomy, stomas and open versus laparoscopic versus robotic approaches are planned is in Colon Cancer Surgery in India. It is not a rectal-cancer page: radiation has a much larger role when the tumour is rectal. See rectal cancer surgery.
International patients comparing surgical oncologists, surgical gastroenterologists and gastroenterologists commonly start with Delhi NCR, Mumbai, Bengaluru, Chennai and Hyderabad. Partner surgical-oncology hospitals in Delhi NCR and Mumbai are a typical first filter.
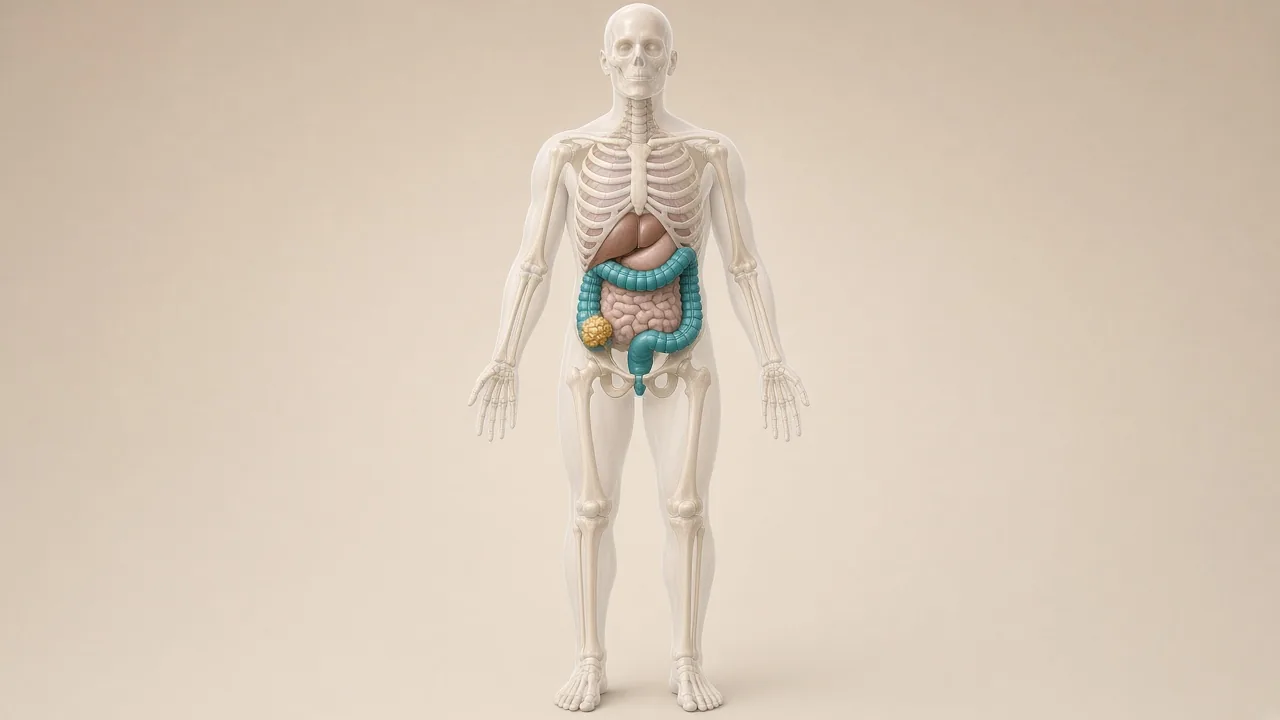
What Is Stage 1 Colon Cancer?
Stage 1 colon cancer is an early form of invasive colon cancer. The cancer has grown beyond the innermost lining of the colon but has not spread to regional lymph nodes or distant organs.
Stage 1 colon cancer is generally classified as T1 or T2 + N0 + M0, where T1 means the cancer has grown into the submucosa, T2 means it has grown into the muscularis propria, N0 means no regional lymph-node metastasis has been identified, and M0 means no distant metastasis has been identified. The American Cancer Society classifies Stage I colon cancer as T1 or T2, N0, M0 disease.
Stage 1A vs Stage 1B Colon Cancer
Patients may come across terms such as Stage 1A and Stage 1B when researching colon cancer. The exact terminology can vary according to the staging system being used. For practical treatment decisions, the important issue is the depth of tumour invasion and whether the cancer has spread to lymph nodes or distant organs.
| Tumour category | Depth of invasion | Lymph nodes | Distant spread |
|---|---|---|---|
| T1 | Submucosa | N0 | M0 |
| T2 | Muscularis propria | N0 | M0 |
The patient's final stage should always be taken from the pathology and staging assessment rather than inferred from tumour size alone.
What does T1 colon cancer mean?
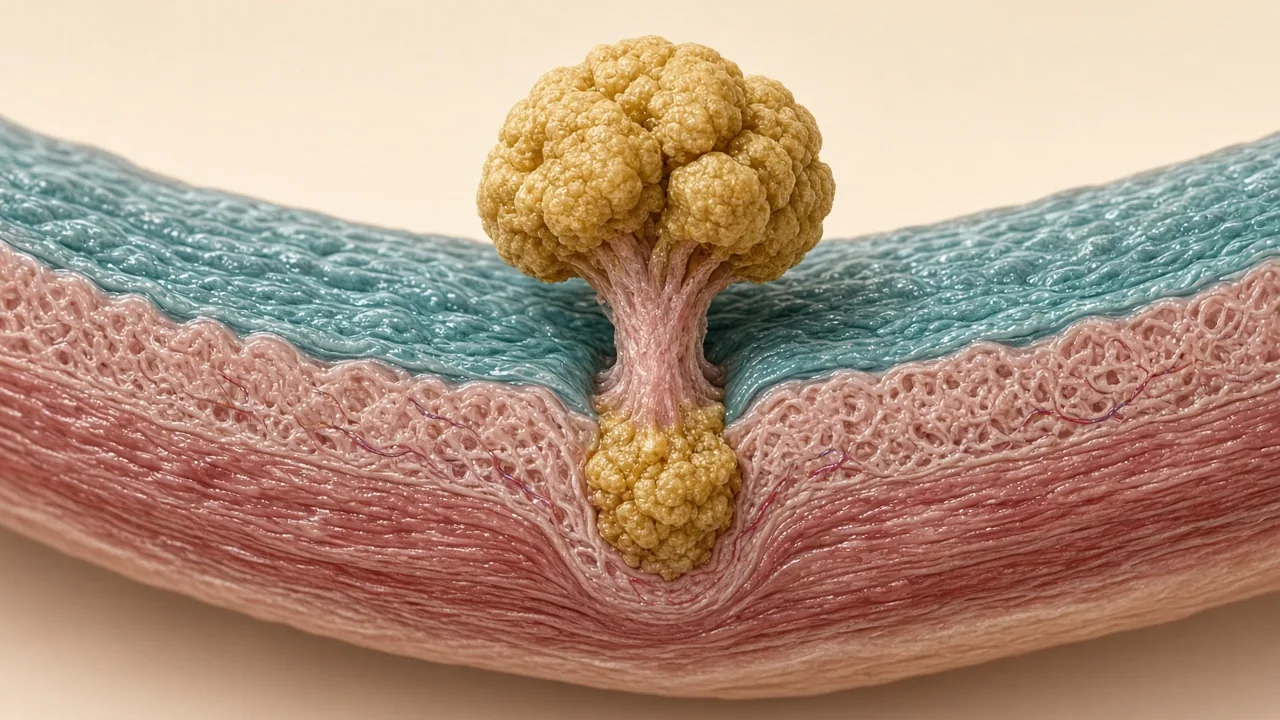
T1 colon cancer has grown through the innermost lining of the colon and into the submucosa. It has not invaded the muscularis propria. Some T1 cancers, particularly those discovered within polyps, may be suitable for complete endoscopic removal. However, this depends on the pathology.
What does T2 colon cancer mean?
T2 colon cancer has invaded the muscularis propria, the main muscle layer of the colon wall. Because the cancer has penetrated deeper into the bowel wall, formal surgical resection with regional lymph-node removal is generally required.
How Is Stage 1 Colon Cancer Diagnosed?
Colonoscopy allows a doctor to examine the lining of the entire colon. A suspicious lesion can be biopsied, removed if appropriate, measured, localised and examined for additional polyps. If cancer is found within a polyp, the complete pathology of that polyp becomes especially important.
The pathology report provides information that cannot be obtained from a scan alone. It may describe cancer type, tumour differentiation, depth of invasion, margin status, lymphovascular invasion, perineural invasion, tumour budding and other microscopic characteristics. For a cancer removed through colonoscopy, these findings can determine whether the patient needs additional surgery.
Why Is the Pathology Report So Important?
A colonoscopy may identify a cancerous polyp. The pathology report helps answer a much more important question: has the cancer been completely removed, and is there a significant risk that cancer remains elsewhere in the bowel or lymphatic system?
The decision about additional surgery may depend on margin status, depth of invasion, tumour differentiation, lymphovascular invasion, tumour budding and other pathological risk factors. Therefore, not every Stage 1 cancer found in a polyp automatically requires colectomy. Likewise, not every cancerous polyp can be considered completely treated after polyp removal.
Can Stage 1 Colon Cancer Be Removed During Colonoscopy?
Yes, in selected patients. A cancer arising within a polyp may sometimes be completely removed during colonoscopy. Potential endoscopic techniques include polypectomy, endoscopic mucosal resection and selected advanced endoscopic resection techniques.
If the cancer has been completely removed and the pathology shows favourable characteristics, additional surgery may not be necessary. However, the decision must be based on the complete pathology report.
When is endoscopic removal enough?
Endoscopic treatment may be sufficient when the lesion has been completely removed, the margins are appropriately clear, the depth of invasion is favourable, there are no significant high-risk pathological features, and the pathology can be reliably assessed. If the cancer has high-risk features, formal colon surgery may be recommended.
When is surgery needed after polyp removal?
Additional surgery may be recommended when the pathology indicates a significant risk of residual disease or lymph-node involvement — for example cancer at the resection margin, incomplete removal, unfavourable or uncertain margins, deep submucosal invasion, lymphovascular invasion, poor tumour differentiation or other high-risk pathological features. The objective of surgery is to remove the potentially involved section of colon and regional lymph nodes.
What Is the Standard Surgery for Stage 1 Colon Cancer?
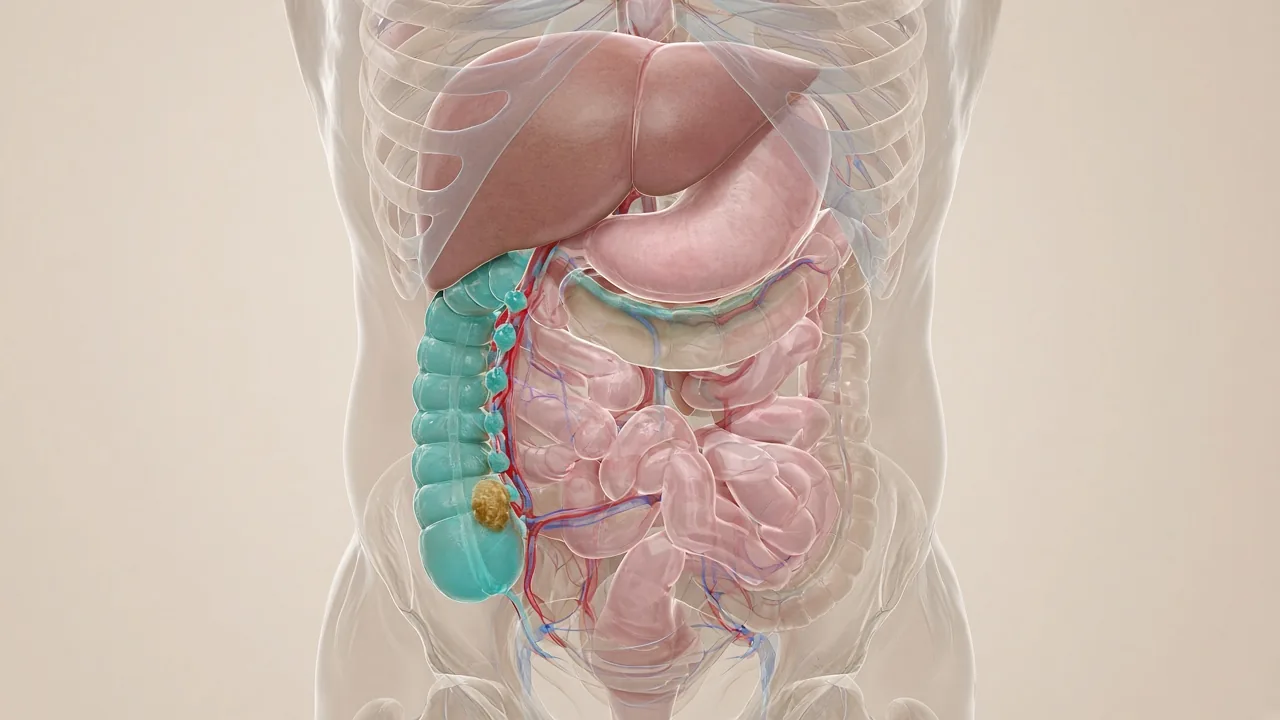
For Stage 1 colon cancer requiring formal surgery, the usual procedure is a partial colectomy. The operation removes the section of colon containing the cancer, an appropriate margin of surrounding tissue, and regional lymph nodes. The remaining bowel is generally reconnected. The exact operation depends on where the cancer is located. See Colon Cancer Surgery in India for hemicolectomy types, anastomosis, stomas and approach choice.
Types of surgery
Right hemicolectomy is used for selected cancers involving the caecum, ascending colon, hepatic flexure or some proximal transverse-colon tumours. Extended right hemicolectomy removes more of the colon when a wider oncological resection is required. Left hemicolectomy may be used for the descending colon, splenic flexure or selected distal transverse-colon tumours. Extended left hemicolectomy may be considered around the splenic flexure. Sigmoid colectomy removes the sigmoid segment. Transverse colectomy removes a portion of the transverse colon; an extended colectomy is sometimes preferred.
| Tumour location | Possible operation |
|---|---|
| Caecum | Right hemicolectomy |
| Ascending colon | Right hemicolectomy |
| Hepatic flexure | Right or extended right hemicolectomy |
| Transverse colon | Transverse or extended colectomy |
| Splenic flexure | Left or extended left hemicolectomy |
| Descending colon | Left hemicolectomy |
| Sigmoid colon | Sigmoid colectomy |
This is a general guide. The actual operation depends on the patient's anatomy, tumour characteristics and surgical assessment.
Open, Laparoscopic or Robotic Surgery

Laparoscopic colectomy uses several small abdominal incisions, a camera and specialized instruments. Potential benefits include smaller incisions, reduced wound discomfort, earlier mobility, faster recovery for many suitable patients and smaller scars. It is an established option for appropriately selected colon cancer patients.
Robotic-assisted surgery is available at selected hospitals in India. The surgeon controls the instruments from a console. Potential technical advantages include magnified three-dimensional visualization, articulating instruments, fine instrument control and stable camera positioning. Robotic surgery is not automatically necessary for every Stage 1 patient. The decision should depend on tumour location, surgical complexity, patient anatomy, previous surgery, surgeon expertise and hospital resources.
Open colectomy is performed through a larger abdominal incision. It may be appropriate when minimally invasive surgery is not suitable, there are extensive adhesions, the patient has had multiple previous abdominal operations, complex anatomy is present, unexpected findings occur, or conversion becomes necessary. The goal remains complete and safe removal of the cancer.
There is no single approach that is best for every patient. Both laparoscopic and robotic surgery are minimally invasive. The more important questions are whether the cancer can be completely removed, whether adequate lymph nodes can be assessed, whether the surgeon is experienced with the selected technique, and why that approach is being recommended.
Are Lymph Nodes Removed in Stage 1 Colon Cancer Surgery?
Yes. Regional lymph nodes are generally removed along with the cancer-bearing segment of the colon. The pathologist examines these lymph nodes under a microscope. This helps confirm the final stage. Lymph-node assessment is important because imaging cannot reliably detect every microscopic lymph-node metastasis.
At least 12 regional lymph nodes is a commonly used benchmark for adequate pathological staging of colon cancer. The actual number retrieved varies between patients. The pathology report should document the total lymph nodes examined and how many contain cancer. If cancer is found in regional lymph nodes, the patient's stage may change.
A patient may initially be considered Stage 1 based on colonoscopy and imaging. After surgery, the removed bowel and lymph nodes are examined under a microscope. If cancer is discovered in regional lymph nodes, the final stage may be higher than the initial clinical stage. This is why the final pathology report is essential.
Is Chemotherapy, Immunotherapy, Targeted Therapy or Radiation Required?
Usually no chemotherapy. For adequately treated Stage 1 colon cancer, chemotherapy is generally not routinely recommended. The American Cancer Society states that patients with Stage I colon cancer generally do not require additional treatment after appropriate surgery. Chemotherapy becomes much more relevant when cancer has spread to regional lymph nodes or distant organs. GAF planning ranges for chemotherapy are $1,500–$8,000+ if it later becomes indicated.
Immunotherapy is not routinely used. It has an important role in selected colorectal cancers, especially certain advanced MSI-H/dMMR tumours, but it is not standard treatment for a completely removed Stage 1 colon cancer. Immunotherapy planning ranges ($15,000–$45,000) apply to those later settings.
Targeted therapy is generally not used after adequate removal of Stage 1 disease. Targeted medicines ($8,000–$30,000) are primarily used in selected advanced or metastatic colorectal cancers.
Radiation therapy is usually not used. It has a much more established role in rectal cancer. For Stage 1 colon cancer, the primary treatment is usually endoscopic removal or surgery. EBRT planning ranges ($1,000–$6,000+) are listed for completeness, not as a Stage 1 standard.
What Happens After Stage 1 Colon Cancer Surgery?
The removed tissue is sent to the pathology department. The final report may include tumour type, size, grade, depth of invasion, surgical margins, number of lymph nodes examined, number of positive lymph nodes, lymphovascular invasion, perineural invasion and other pathological features. The multidisciplinary team then confirms the final stage. For genuinely Stage 1 disease that has been adequately removed, the patient generally moves into surveillance.
R0 resection, margins and high-risk features
An R0 resection means that no microscopic cancer is identified at the surgical margins. Achieving an R0 resection is an important goal of curative cancer surgery. A surgical margin is the edge of the tissue removed; a clear margin indicates that no cancer was identified at the examined surgical edge.
Lymphovascular invasion means cancer cells are identified within lymphatic or blood vessels around the tumour. It can be associated with an increased risk of recurrence and can be relevant when assessing an early cancer removed endoscopically. Perineural invasion occurs when cancer cells are found around or within nerves. Tumour budding describes small clusters of cancer cells at the invasive edge of a tumour. These findings should be interpreted by an experienced gastrointestinal pathologist along with the rest of the pathology report.
Stage 1 Colon Cancer Treatment Pathway in India
A typical pathway is: colonoscopy → biopsy / polyp removal → histopathology → staging assessment → specialist review → endoscopic treatment or colectomy → final pathology → confirmation of final stage → surveillance. For patients requiring surgery: preoperative assessment → colectomy → hospital recovery → final pathology → follow-up.
Preoperative testing may include complete blood count, kidney and liver function, electrolytes, blood glucose, ECG, anaesthesia assessment, colonoscopy, biopsy, CT imaging and CEA testing where appropriate. PET-CT is not routinely required for every patient with Stage 1 colon cancer. MRI is much more important in rectal cancer than in uncomplicated colon cancer.
Hospital Stay and Recovery
There is no fixed operating time. A straightforward colectomy may take several hours. Many patients remain in hospital for several days after an uncomplicated colectomy. GAF planning notes 5–10 nights for colectomy. Enhanced recovery programmes may allow suitable patients to leave hospital earlier.
Recovery generally occurs gradually: pain management, early mobilisation, breathing exercises, nutrition and clot prevention in the first few days; walking and daily activities over the first few weeks; then a progressive return to usual activities. Recovery may take longer after open surgery or if complications occur. There is no single postoperative diet. Immediately after surgery, smaller meals are often tolerated better. Adequate protein and hydration matter more than an unnecessarily restrictive diet.
Most patients undergoing routine Stage 1 colon cancer surgery do not require a permanent colostomy. The need for a stoma depends on tumour location, type of operation, bowel condition, emergency versus planned surgery, and the safety of reconnecting the bowel. Ostomy / stoma surgery planning ranges are $2,500–$6,800 if a stoma is required.
Severe abdominal pain with vomiting, inability to pass stool or gas, sudden abdominal distension, heavy bleeding, chest pain, or collapse after discharge belongs in a local emergency department — not a delayed WhatsApp message.
Follow-Up, Recurrence and Prognosis
Although the risk is generally lower than in advanced colon cancer, recurrence can occur — locally, in regional lymph nodes, in the liver or lungs, or at other distant sites. Follow-up may include clinical assessment, colonoscopy, CEA testing when appropriate and imaging in selected patients.
Stage 1 colon cancer generally has a more favourable prognosis than cancers that have spread to lymph nodes or distant organs. A general survival statistic cannot predict an individual patient's outcome. Prognosis depends on T stage, histology, grade, margins, lymphovascular and perineural invasion, other pathological characteristics and completeness of treatment. Stage 1 colon cancer is generally treated with curative intent. No responsible doctor should guarantee a cure for an individual patient without reviewing the complete pathology and clinical information.
Stage 1 Colon Cancer Treatment Cost in India
There is no single fixed price. The cost depends on whether the patient needs endoscopic treatment or formal surgery, plus hospital, city, surgeon, open/laparoscopic/robotic approach, length of stay, pathology and complications.
| Component | GAF planning range in India |
|---|---|
| Colonoscopy (including selected polypectomy) | $200–$550 |
| Colectomy | $7,000–$18,000 |
| Colorectal cancer surgery | $8,000–$20,000 |
| Ostomy / stoma surgery if required | $2,500–$6,800 |
| Chemotherapy (not routine for Stage 1) | $1,500–$8,000+ |
City pages such as Delhi NCR colectomy, Mumbai, Bengaluru, Chennai and Hyderabad use the same national range unless a hospital issues a verified quotation. Colonoscopy city pages include Delhi NCR colonoscopy and Mumbai colonoscopy.
Before travelling, ask whether the estimate includes surgeon and anaesthetist fees, theatre charges, consumables, room, nursing, medicines, routine investigations, pathology and follow-up — and what is excluded (complications, extended ICU, additional surgery, extra pathology, molecular testing, blood products, extended stay).
How to Choose a Hospital and What to Ask
Look for experienced colorectal surgeons, GI surgical oncology, gastroenterology, expert gastrointestinal pathology, modern imaging, laparoscopic surgery, robotic surgery where appropriate, medical oncology, anaesthesia and critical-care support, and multidisciplinary cancer care. The presence of robotic technology should not be the primary reason for choosing a hospital.
- Is my cancer definitely Stage 1, and is it T1 or T2?
- Was the cancer completely removed during colonoscopy, and are the margins clear?
- Does the pathology show any high-risk features that would prompt a colectomy?
- Which part of the colon and how many lymph nodes will be removed, and will the approach be open, laparoscopic or robotic?
- Will I need a stoma, how long is hospital stay, and will I need chemotherapy?
- What surveillance will I need, what is the estimated total cost, and what happens if a complication occurs?
Stage 1 Colon Cancer: Endoscopic Removal vs Surgery
| Feature | Endoscopic removal | Colectomy |
|---|---|---|
| Typical use | Selected early cancers within suitable polyps | Cancers requiring formal resection |
| Major bowel resection | No | Yes |
| Lymph nodes removed | No | Yes |
| Hospital stay | Usually short | Usually several days |
| Recovery | Generally quicker | Several weeks |
| Further treatment | Depends on pathology | Depends on final pathology |
The most important point is that endoscopic removal is only sufficient when the complete pathology supports it.
The Bottom Line
Stage 1 colon cancer is an early cancer that has not been identified in regional lymph nodes or distant organs. The central treatment question is: has the cancer been completely removed with a sufficiently low risk of residual disease or lymph-node involvement?
For selected cancers found within polyps, complete endoscopic removal may be enough. When endoscopic treatment is not adequate, a partial colectomy with regional lymph-node removal is generally the standard treatment. For most adequately treated Stage 1 colon cancers the sequence is complete endoscopic removal or surgery → final pathology → surveillance, rather than surgery → routine chemotherapy. Chemotherapy, immunotherapy and targeted therapy are not routine treatments for an otherwise adequately treated Stage 1 colon cancer.
Frequently Asked Questions
What is the main treatment for Stage 1 colon cancer?
The main treatment is complete removal of the cancer. Selected early cancers can be removed endoscopically, while others require partial colectomy.
Is Stage 1 colon cancer curable?
Stage 1 colon cancer is generally treated with curative intent when the cancer can be completely removed.
Does Stage 1 colon cancer require chemotherapy?
Usually not. Chemotherapy is generally not routinely recommended after adequate treatment of Stage 1 colon cancer.
Can Stage 1 colon cancer be removed during colonoscopy?
Yes. Selected cancers arising in polyps may be completely removed during colonoscopy.
When is colectomy required?
Colectomy may be recommended when the cancer cannot be adequately removed endoscopically or when pathology shows features associated with a significant risk of residual cancer or lymph-node involvement.
What is the difference between T1 and T2 colon cancer?
T1 cancer has invaded the submucosa. T2 cancer has invaded the muscularis propria. Both can be Stage 1 when there is no lymph-node or distant spread.
Is robotic surgery necessary?
No. Robotic surgery can be appropriate in selected cases, but laparoscopic or open surgery may also be appropriate.
How many lymph nodes are removed?
Regional lymph nodes are removed during formal colectomy. At least 12 examined lymph nodes is a commonly used benchmark for adequate pathological staging.
Will I need a colostomy?
Most patients undergoing routine Stage 1 colon cancer surgery do not require a permanent colostomy.
How long does recovery take?
Recovery varies, but many patients gradually return to normal activities over several weeks. GAF planning notes for colectomy are typically 5–10 nights in hospital.
Is radiation therapy used?
Usually not. Radiation is much more commonly used for rectal cancer.
Is immunotherapy used?
Not routinely for adequately treated Stage 1 colon cancer.
Is PET-CT required?
Not routinely for every Stage 1 colon cancer patient.
What happens after surgery?
The removed tumour and lymph nodes are examined by a pathologist. The final pathology determines the final stage and follow-up plan.
How much does Stage 1 colon cancer treatment cost in India?
The cost depends on whether endoscopic treatment or colectomy is required. GAF planning ranges include approximately $200–$550 for colonoscopy and $7,000–$18,000 for colectomy. An individualized quotation is more reliable than a single national average.
Can international patients receive Stage 1 colon cancer treatment in India?
Yes. International patients can have their medical records reviewed by Indian specialists before travelling and can arrange consultation, treatment and follow-up.
Related Colon Cancer Resources
- Colon Cancer Targeted Therapy in India — RAS, BRAF V600E, HER2, KRAS G12C, cetuximab, bevacizumab and later-line options.
- Colon Cancer Immunotherapy in India — MSI-H/dMMR testing, pembrolizumab, nivolumab plus ipilimumab and immune-related side effects.
- Colon Cancer Chemotherapy in India — FOLFOX vs CAPOX, 3 versus 6 months, FOLFIRI and when immunotherapy comes first.
- Stage 4 Colon Cancer Treatment in India — metastatic disease, resectability, conversion therapy and biomarker-directed treatment.
- Stage 3 Colon Cancer Treatment in India — node-positive disease, FOLFOX/CAPOX and 3 versus 6 months of adjuvant chemotherapy.
- Stage 2 Colon Cancer Treatment in India — deeper wall invasion, high-risk features and the chemotherapy discussion.
- Colon Cancer Treatment in India — stage, molecular tests and systemic medicines around early disease.
- Colon Cancer Surgery in India — hemicolectomy types, anastomosis, stomas and approach choice.
- Colectomy cost in India — GAF planning range $7,000–$18,000.
- Colonoscopy cost — $200–$550 planning range for selected polypectomy.
- Colorectal cancer surgery cost — $8,000–$20,000 planning range.
- Rectal cancer surgery — a different pathway when radiation may be part of treatment.
- Breast cancer treatment in India and prostate cancer treatment in India — other GAF cancer pathways.
How GAF Healthcare Can Help
GAF Healthcare coordinates international patients who need a Stage 1 colon cancer opinion in India — after a malignant polyp, a T1 or T2 report, or a recommendation for colectomy. Share the colonoscopy PDF, the complete pathology report, CT files and CEA. A coordinator can introduce a gastroenterologist or surgical oncologist and help collect an itemised quotation covering endoscopic treatment or the operation, stay and pathology.
Medical Disclaimer
This article is intended for general educational purposes and should not replace consultation with a qualified colorectal surgeon, gastroenterologist or medical oncologist. Stage 1 colon cancer treatment is highly individualized. Whether endoscopic removal is sufficient, whether a colectomy is required, and whether any additional treatment is needed depends on the complete pathology, imaging, previous treatment and overall health. Patients should not start, stop or change cancer treatment without discussing it with their treating doctor.
Top 10 Sources
- NCI — Colon Cancer Treatment (PDQ®) — staging and treatment options by stage.
- American Cancer Society — Treatment of Colon Cancer, by Stage — Stage I surgery without routine additional treatment after appropriate resection.
- American Cancer Society — Colorectal Cancer Stages — T, N and M classifications and Stage I disease.
- NCCN — Colon Cancer Guidelines — professional guidance for colon cancer management.
- ASCRS — Clinical Practice Guidelines — colorectal surgical management.
- ASCO — Gastrointestinal cancer guidelines — evidence-based oncology guidance.
- ICMR — Consensus Document for Management of Colorectal Cancer — India-specific diagnosis and management.
- ESMO — Gastrointestinal cancer guidelines — European guidance for colon cancer treatment.
- Cancer Research UK — Types of surgery for bowel cancer — local resection, colectomy, recovery and complications.
- American Cancer Society — Surgery for Colon Cancer — partial colectomy, lymph-node removal and surgical approaches.
Last reviewed against the cited sources: September 2026.